 800-861-9372


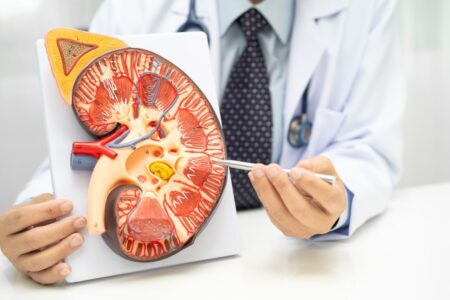
Surviving a drug overdose is not always the end of the medical emergency. A new CDC analysis of nearly 1.3 million overdose hospitalizations found that one third of patients developed acute kidney injury, and most of those patients went on to dialysis, respiratory failure, shock, or death in the hospital. For people with opioid addiction, the injury adds a long-term risk that standard overdose statistics do not capture.
The study, published in the agency’s Morbidity and Mortality Weekly Report, examined hospital discharge records from 2016 to 2025 in the Premier Healthcare Database, which covers roughly 1,400 hospitals and about 25 percent of annual U.S. inpatient admissions. Researchers tracked overdoses involving opioids, cocaine, or psychostimulants, the drug classes most common in U.S. overdose deaths.
What the CDC Found in 1.3 Million Overdose Hospitalizations
Among 1,297,847 drug overdose hospitalizations, 448,136 patients, or 34.5 percent, were diagnosed with acute kidney injury. Of those patients, 273,093, or 60.9 percent, experienced what researchers classified as a severe inpatient course, meaning acute dialysis, respiratory compromise, shock or hypotension, or in-hospital death.
Acute kidney injury is a sudden loss of kidney function that raises the later risk of chronic kidney disease, kidney failure, and death. The report cites cost estimates of $1,795 in additional costs per hospitalization for the injury and $11,016 more when dialysis is required.
Kidney Injury Hit Younger Overdose Patients Hardest
Older patients were more likely to develop kidney injury after an overdose, at 37.4 percent of patients 65 and older compared with 28.2 percent of patients 24 and younger.
The pattern reversed for severity. Among patients who did develop kidney injury, 68.1 percent of those 24 and younger had a severe inpatient course, the highest of any age group, compared with 56.1 percent of patients 65 and older.
Men developed kidney injury at a higher rate than women, 38.1 percent against 29.4 percent, while women with kidney injury were slightly more likely to take a severe course, 61.9 percent against 60.4 percent. The report notes younger patients may face more cumulative years at risk for chronic kidney disease after an overdose-related injury.
Overdose Kidney Injury Rates Turned Down After 2022
The share of overdose hospitalizations involving kidney injury rose from 2016 to 2022 at an annual rate of 2.69 percent, then fell from 2022 to 2025 at an annual rate of 5.11 percent.
Severe inpatient courses among kidney injury patients climbed from 2016 to 2023 at 1.82 percent a year before declining 2.89 percent a year through 2025. The downturn tracks the same period in which U.S. overdose deaths began to decline.
The authors write that overdose-related kidney injury may be partly preventable, because it follows an identifiable exposure. They point to expanded naloxone distribution, wider access to substance use treatment, and timely medical evaluation after a suspected overdose as the levers that reduce it.
Follow-Up Kidney Care After Overdose Lags Behind
The report urges hospitals to link overdose patients with kidney injury to postdischarge kidney care and to substance use treatment that can prevent the next overdose.
Naloxone and Opioid Addiction Treatment as Prevention
Naloxone, sold under brand names including Narcan, reverses an opioid overdose when given in time, and wider retail availability since 2019 may have shifted which overdoses end in hospitalization at all.
For people who do reach the hospital, medications for opioid addiction, including buprenorphine and methadone, cut the risk of a repeat overdose, and peer support through Narcotics Anonymous meetings helps many people sustain recovery after discharge.
Families can find NA meetings near them and learn about opioid treatment programs through Narcotics.com, which also covers harm reduction tools like naloxone distribution and fentanyl test strips. Call 800-934-1582(Sponsored) to learn more about treatment options near you.
A synthetic opioid up to 100 times more potent than fentanyl is retreating from the U.S. drug supply, at least for now. A new situation summary from the Centers for Disease Control and Prevention, published November 9, 2026, shows carfentanil detections in overdose deaths and drug seizures falling after a peak in the second half of 2025.
Carfentanil is a fentanyl analog, and it remains rare in the illegal drug supply, where it is primarily found mixed with illicitly made fentanyl. Even trace exposure carries outsized danger because of the drug’s strength.
A Drug That Nearly Vanished, Then Returned
Carfentanil caused severe localized overdose outbreaks in the past, then almost disappeared from the American drug supply during 2021 and 2022.
Detection among overdose deaths began climbing again in 2023, rising from 0.02 percent of deaths in the first quarter of that year to 3.20 percent during July through September 2025. The CDC’s updated tracking shows that percentage declining into 2026.
Urine drug testing told the same story. Among specimens that tested positive for fentanyl, the share also positive for carfentanil peaked at 1.73 percent during July through September 2025 before falling.
Testing of illegal drug products and paraphernalia peaked later, during July through December 2025, then decreased during the first half of 2026.
Midwest and Northeast See the Sharpest Spikes
The resurgence was not evenly distributed. The CDC found sharper increases in carfentanil detection among fentanyl-positive urine specimens in the Midwest beginning in 2025.
During the second half of that year, four jurisdictions reported carfentanil in 5 percent or more of illegal opioid samples, and all four were in the Midwest and Northeast.
By January through June 2026, the number of sentinel jurisdictions detecting carfentanil in opioid-positive drug samples had dropped from 13 to 9 out of 15 sites reporting.
Detection across all census regions decreased from the mid-2025 peak into early 2026, though the Midwest, Northeast, and West each saw slight upticks between the first and second quarters of 2026.
Why One Dose of Naloxone May Not Be Enough
The CDC’s guidance for bystanders reflects the drug’s potency. Because carfentanil is so strong, multiple doses of naloxone or additional medical care might be required to reverse an overdose.
Overdose symptoms match those of other opioids: slowed or stopped breathing, drowsiness, disorientation, sedation, pinpoint pupils, and clammy skin. Because of its potency, even small amounts can increase the risk of overdose.
How the CDC Tracks an Emerging Threat
The situation summary draws on three data streams. Urine drug tests conducted by Millennium Health track exposure among patients in behavioral health, primary care, and substance use treatment settings.
The State Unintentional Drug Overdose Reporting System captures postmortem toxicology from 40 funded jurisdictions. Laboratory testing by 18 local public health departments, with 15 reporting complete data, provides early warning of changes in the drug supply itself.
The CDC says it will update the summary every six months, a sign that officials expect carfentanil to remain a moving target. If you or someone in your life uses opioids, carry naloxone, learn the signs of an overdose, and understand that a rescue may take more than one dose.
You can search Narcotics.com’s directory to find NA meetings near you. Call 800-934-1582(Sponsored) to get in contact with a treatment advisor today.

Broken sleep does more than leave people groggy. New research published in Drug and Alcohol Dependence found that perceived sleep disruption was tied to stronger opioid craving and higher daily opioid doses among adults with chronic low back pain, a pattern clinicians see as one pathway into opioid addiction for people on long-term opioid therapy.
What Researchers Measured in Chronic Pain Patients
The study followed 81 adults with chronic low back pain who were receiving long-term opioid therapy. For 14 days, participants completed ecological momentary assessment, a method that captures real-time reports on a phone or device, along with overnight actigraphy monitoring that tracks movement during sleep.
The research was supported by the National Institute on Drug Abuse Intramural Research Program. The team, led by Eleanor Blair Towers, focused on wake after sleep onset, the minutes spent awake during the night after first falling asleep.
They measured it two ways, through sleep diaries and through actigraphy, and tracked morning and nocturnal craving, pain severity, and daily opioid dose in morphine milligram equivalents. Fourteen days of per-person data gave the researchers an unusually detailed view of how nights and doses connect.
Sleepless Nights Fed Craving and Higher Doses
Greater diary-based wake after sleep onset was associated with higher nocturnal opioid craving. Pain severity proved a strong predictor of both nocturnal and morning craving, and it changed the relationship between sleep and dose. On high-pain days, more time awake at night was linked to a higher opioid dose the following day.
Actigraphy-derived sleep measures, by contrast, showed minimal association with craving or dose, which means the subjective experience of bad sleep may matter more than the objective movement data.
The scope of the issue is large. Chronic low back pain affects more than 600 million people worldwide, and many receive long-term opioid therapy, according to the study’s authors.
Why Craving Matters in Opioid Addiction Risk
Craving is not just discomfort. It is a recognized warning sign in the development of opioid addiction, and it can push prescribed use toward opioid abuse when doses climb beyond what a clinician intended.
This study gives patients and providers a concrete, modifiable target: treating sleep problems may interrupt the cycle before escalating use takes hold.
The findings also carry weight for the broader overdose crisis. People whose prescribed opioid use spirals sometimes transition to unregulated narcotics, where fentanyl now dominates the supply and raises the lethality of every dose. Catching craving early, at the level of sleep and pain management, is upstream prevention.
That framing shifts a routine part of pain care into a relapse-prevention opportunity. A patient who reports waking for long stretches at night is giving their prescriber actionable information, and treating the sleep problem directly may reduce the craving that drives dose escalation.
Sleep as a Treatment Target in Pain Care
The authors describe sleep disturbance as a potentially modifiable intervention target in chronic pain populations. For people on long-term opioid therapy, that opens practical conversations with prescribers about insomnia treatment, cognitive behavioral therapy for sleep, and pain management plans that do not depend solely on dose increases.
Finding Help for Opioid Dependence
Anyone who notices craving building between doses, or who takes more opioid medication than prescribed, can treat that as useful information rather than a personal failure.
Medication-assisted treatment with buprenorphine or methadone stabilizes craving, and naloxone should be on hand for anyone using opioids in any form.
Peer support through Narcotics Anonymous is free and available in most communities, and people looking for NA meetings near them can search local helplines and online meeting locators any hour of the day. Call 800-934-1582(Sponsored) to speak with a treatment specialist and learn more about your options.

A physician’s new argument for classifying kratom as an opioid might open eyes concerning its addictive properties. Dr. Andrew Kolodny of Brandeis University’s Opioid Policy Research Collaborative relayed that folks consuming substantial amounts of mitragynine or semisynthetic kratom opioids clinically resemble patients he has treated for oxycodone, heroin or fentanyl addiction.
Kolodny and Dr. Christopher P. Holstege of the University of Virginia School of Medicine discussed the classification argument.
The Classification Debate
Kratom is a botanical substance with stimulant-like effects at low doses and opioid-like effects at higher doses. Kolodny argues that calling its effects opioid-like implies that it’s not an opioid and downplays the dependence and addiction clinicians are seeing.
Kolodny’s Reports
Since 2025, Kolodny noted that nearly every patient he encountered with newly developed opioid addiction had become addicted while taking kratom. Colleagues in other parts of the country reported a similar increase.
Some patients had moved from kratom leaf products to deadlier semisynthetic products. Kolodny described withdrawal severe enough that some patients’ overall clinical presentations were comparable to those associated with heroin or fentanyl addiction.
Patients were routinely treated with buprenorphine. Recovery without buprenorphine may be possible for those with shorter durations of addiction or lower-dose use. Treatment depends on the person’s use pattern, withdrawal history, health and response to previous attempts to stop.
Kolodny noted how the kratom industry promotes products as non-opioid, non-addictive and as safe alternatives. However, his findings have suggested otherwise.
Treatment & Withdrawal
Buprenorphine is one medication for opioid use disorder. It reduces withdrawal and cravings and might be a good fit rather than turning to unregulated kratom.
People who use kratom alongside opioids should disclose their history to a clinician. Polysubstance use can change overdose and withdrawal risks. Naloxone can reverse opioid overdoses and emergency help is needed for slowed breathing, unresponsiveness or other overdose signs.
Peer support accompanies medical care. Narcotics Anonymous meetings are free and open to people with different substance use histories. NA doesn’t replace prescribing or withdrawal management and meds and meetings often go together.
NA Still a Top Tier Option
If kratom use feels difficult to control or stopping causes withdrawal, a clinical assessment can clarify treatment options.
Alongside clinical care, NA meetings offer constant camaraderie and fellowship. You won’t have to go through any step alone. Rather, educational resources on opioid addiction and friendly shoulders can make the tough times pass a little easier.
To get started, simply browse our directory for NA chapters anywhere in the USA. You can also dial 800-934-1582(Sponsored) to chat with an expert.

The Topeka City Council approved $300,000 for a homeless outreach program built around opioid addiction as a root cause of homelessness. They’ll fund daily field workers to connect folks on the street to case management, clinical services, and treatment.
The program is led by the nonprofit Breakthrough House. Even though Kansas has many programs like local Narcotics Anonymous chapters to to assist those impacted by opioid addiction, the unhoused has few dedicated services.
Opioids & Homelessness in Topeka
Kim Williams-Gaston is chief operating officer of Breakthrough House. She pointed out the city’s homeless population is large and growing .
Local leaders estimate that a significant part of Topeka’s homeless population has opioid addiction. That’s why the outreach effort revolves around both problems.
Outreach is In
Carrie Higgins, director of the city’s housing services division, relayed that they want to get people diagnosed and quickly connected to treatment that fits their situation.
WIlliam-Gaston added that the program also connects participants to housing and a clubhouse where they can build daily living and job skills.
The initiative operates in the Built for Zero framework. They coordinate action to reduce homelessness and prevent it when possible. Indeed, success is measured against Built for Zero national standards to get the number down to zero.
Harm Reduction & Treatment
Outreach programs that engage people actively using opioids increasingly pair treatment connections with harm reduction tools.
Naloxone reverses opioid overdoses and is safe to administer.
Medication-assisted treatment, which combines FDA-approved medications with counseling, remains the standard of care for opioid addiction and sharply reduces overdose risk when people stay in treatment.
NA Meetings in Amerca’s Heartland & Beyond
Long-term recovery often depends on ongoing peer support after formal treatment ends. Narcotics Anonymous meetings give people a free, regular structure for staying connected, and meetings exist across Topeka and the rest of Kansas.
If you or someone you love is struggling, you can find NA meetings in Topeka or anywhere else in the country via our browsable directory.
Call 800-934-1582(Sponsored) is another option to speak with someone about approaches to opioid addiction treatment..

Ohio officials now contend with a synthetic opioid that most folks haven’t heard of until an overdose hits. Nearly 50 overdoses in the last three months involved cychlorphine, which is 100x deadlier than fentanyl.
Even though Ohio has many programs to battle drugs, including Narcotics Anonymous programs on the ground, new drugs up the ante. These cases represent the latest chapter in an opioid addiction crisis that keeps mutating faster than public awareness.
The Opioid Crisis in The Buckeye State
Synthetic opioids already drive the majority of U.S. overdose deaths. Cychlorphine first surfaced in August 2024 and has since surfaced in pills and in powders disguised as other street drugs.
Cychlorphine is a synthetic opioid in the nitrile class and binds powerfully to opioid receptors to suppress breathing. But there’s a hitch. “There’s no smell. There’s no color. You can’t detect it,” staff at the Recovery Institute of Ohio relayed, noting that standard fentanyl test strips don’t pick it up.
Jessica Danner of TruHealing in Cincinnati noted clinicians are seeing the compound arrive alongside other street drugs. “Cychlorphine is the new wave.”
Naloxone Still Works
Since cychlorphine acts on opioid receptors, naloxone can reverse an overdose involving it. But a single standard dose may not be enough against a drug this potent. The guidance remains the same:
- Give naloxone immediately if an overdose is suspected and give additional doses if the person doesn’t respond.
- Call 911 every time. Overdose reversal bought by naloxone is temporary.
- Ohio’s Good Samaritan protections apply when someone seeks emergency help during an overdose.
Enroll in NA
Another option is to use medications for opioid use disorder to blunt cravings and block the lethal respiratory effects of street opioids.
Start with Narcotics Anonymous to find solidarity among your peers. Meetings are free and open to all. To get started, simply browse our directory for chapters anywhere in the USA.
For guidance for local options, dial 800-934-1582(Sponsored) to chat with an expert.

A new class of synthetic opioids is spreading through the US illicit drug supply as the fentanyl era shifts, and it’s accelerating. Orphine analogs were detected in 22 states. The first on the list is cychlorphine, first detected in 2024 and is the most common orphine listed in the United Nations Office on Drugs and Crime early-warning system.
“The findings provide timely evidence of orphine analogues as an emerging drug threat in the US illicit drug supply,” wrote the investigative team at Virginia Commonwealth University School of Medicine in Richmond.
Orphines in the Storm
Researchers analyzed biospecimens collected through the Center for Forensic Science Research and Education’s NPS Discovery early-warning program from 2020-2026. Of 14,261 specimens tested, 142 were positive for orphines, about 1%.
The pattern consisted of two waves. The first in 2020 was dominated by brorphine. A second larger wave began in 2025. Cychlorphine accounted for 100 of 102 orphine cases.
Geographically, 53% of positive specimens originated in the South and 37% in the Midwest. Tennessee placed first with 50 specimens, followed by Illinois with 37, Texas with 14 and Minnesota with 10. All detections in Tennessee and Texas involved cychlorphine, while Minnesota’s involved brorphine and Illinois showed a mixture.
Drivers of the Trend
In July 2025, China generically scheduled nitazene analogues, disrupting supply chains. Cychlorphine specimens rose rapidly immediately afterwards and only a minority of orphine specimens contained nitazene-related compounds. Suppliers facing pressure on one class of synthetic opioid appear to have pivoted to another.
Scheduling has slowly followed. Brorphine is permanently on Schedule I. In August 2026, the DEA moved cychlorphine, spirochlorphine and SR-17018 into Schedule I under a temporary order until August 2028. Four of the five analogues analyzed are on the Controlled Substances Act’s Schedule I list.
Orphines Compared to Fentanyl
Orphine analogues are mu-opioid receptor agonists that first arrived in pharmaceutical programs back in the 1960s. Some are up to 10x deadlier than fentanyl and cause respiratory depression.
Polysubstance exposure was the norm rather than the exception. Benzodiazepine-related compounds appeared in 37% of orphine specimens, fentanyl and methamphetamine or other amphetamines in 36% and cocaine-related compounds in 20%. Nitazenes showed up in 9%, medetomidine in 11% and xylazine in 8%. That mixing raises the risk of fatal overdoses since the depressants compound each other.
Standard Testing Misses Them
The authors called for clinical guidance on managing Cychlorphine and other overdoses, greater access to testing and naloxone and looking out for additional analogues.
They cautioned that submitted specimens came through random and for-cause testing and weren’t systematically drawn from all jurisdictions. So the findings might not be nationally representative.
Harm Reduction & Treatment
Naloxone remains the recommended first response for any suspected opioid overdose, and people who use any street substance should carry it. High-potency opioids can require repeated naloxone doses and close monitoring for re-sedation and calling 911 remains essential.
Medication-assisted treatment remains one of the most effective care programs to thwart withdrawal.
Peer support through Narcotics Anonymous meetings is free and available in most communities. NA works alongside medical treatment.
About NA
Narcotic addictions are treatable, so don’t wait for a crisis to hit. NA remains a first step to a healthier future, and the process is made simpler with our searchable directory organized by city and format.
You can also chat with an expert by dialing 800-934-1582(Sponsored) to explore opioid treatment programs that offer medication-assisted treatment.

Diagnoses of opioid addiction among commercially insured Americans climbed 32.7% between 2022 and 2025, according to FAIR Health’s Opioid Tracker’s report. The national rate rose from 449 patients per 100,000 in 2022 to 596 per 100,000 in 2025.
The Opioid Tracker is a free interactive map of opioid use disorders among commercially insured patients.
The Opioid Crisis Continues
State-level variation is stark. Tennessee recorded the highest rate of commercially insured patients receiving treatment for opioid addiction at 1,551 patients per 100,000. After Tennessee came West Virginia at 1,528, Mississippi at 1,373, Arkansas at 1,320 and Delaware at 1,256. Even though all top five states have access to inpatient care and local Narcotics Anonymous chapters at the community level, each had more than twice the national rate.
Middle aged adults accounted for the largest share at 28%t of the national age distribution, and males made up 56% of diagnosed patients versus 43% female.
In general, opioid addiction is a chronic condition from prescription painkillers, heroin or illicit fentanyl. It changes brain chemistry in ways that make stopping without support extremely difficult. Withdrawal and overdose risk both rise after periods of reduced tolerance. The condition is diagnosed clinically and effective treatment combines medication with counseling rather than relying on willpower alone.
Changes in the Flow
The tracker shows where treatment dollars actually flow. Nationally, alcohol and substance abuse services accounted for 39% of all claim lines carrying an opioid use disorder diagnosis in 2025. The single highest-cost procedure was the weekly methadone medication-assisted treatment bundle, which made up 9.4%.
The treatment workforce is shifting too. Nurse practitioners were the fastest-growing specialty involved in drug treatment, with their share up 67% in 2025, followed by psychiatric nurses at 47% and emergency medicine at 44%. That expansion matters in rural counties hit hardest by fentanyl and other street opioids, where physician shortages have limited access to meds.
Rising diagnosis rates also reflect more folks developing opioid addiction and being identified and connected to care, and the claims data alone cannot separate the two effects.
Harm Reduction & Treatment
Medication-assisted treatment remains the standard for opioid addiction. Tracker data shows it reaches more patients through a broader mix of providers.
Carrying naloxone remains essential for anyone using street opioids, since fentanyl and its replacements continue to drive unpredictable potency.
Peer support through Narcotics Anonymous meetings is free, anonymous and available in most communities.
NA Still a Top Tier Option
Opioid addiction responds to treatment, and the growing workforce numbers suggest care is becoming easier to reach. Feel free to browse our directory to find meetings filtered by location and format.
Call 800-934-1582(Sponsored) to speak with an expert and to explore local options.

Hamilton County in Tennessee hit 89 overdose-related opioid deaths up to September 2026. That compares with 141 deaths reported for 2025. Fentanyl was involved in six out of 10 deaths in the county’s midyear report.
To be clear, Tennessee and its sister states have resources to combat narcotics, including local Narcotics Anonymous chapters in most neighborhoods. Nevertheless, too many people still die.
The Tennessee Council for Recovery and the American Addiction Recovery Association responded to the numbers with outreach teams. Volunteers distributed naloxone, clothing and essential supplies and spoke with community members about recovery.
Meet People Where They Are
Outreach volunteers included folks with addiction and recovery experience. Participants also worked to reduce stigma by treating addiction as a medical condition rather than a moral failure. Maurice Draine, a territory manager involved in the effort, relayed, “I’m just here to get you the help you need, want, and deserve.”
Naloxone Access Matters
Naloxone can reverse an opioid overdose if administered quickly. Distributing it through street outreach makes the medication available to folks who don’t feel comfortable entering a clinic or treatment office.
Fentanyl is a synthetic opioid that’s deadlier than many other opioids. Its ubiquitousness shows why public health agencies emphasize education and naloxone access.
People may not be ready or able to visit a clinic, treatment office or recovery meeting. Street outreach lowers that barrier by bringing supplies and peer support. Volunteers with recovery experience speak without judgment. The Chattanooga effort combined naloxone with basic essentials and tickets intended to connect people with recovery resources.
Naloxone meets the immediate risk of overdose, while conversation and peer support encourage an overdose survivor to find care. Otherwise, they may face the same risk again after leaving the emergency department.
Turn Naloxone Access Into Lasting Recovery
Sustained recovery often requires ongoing support. Treatment may also include medication for opioid use disorder or rehab counseling.
Narcotics Anonymous meetings provide free, peer-led meetings where people can build connection, accountability, and experience with staying drug-free. People looking for local help can search NA meetings via our browsable directory for groups anywhere in the country and compare opioid addiction treatment programs that offer evidence-based care.
Feel free to also dial 800-934-1582(Sponsored) to chat with an expert regarding medication and continuing care after detox or residential treatment.

The first national study of nitazene detections in the United States emphasized the dangers about synthetic drugs circling the streets. Forensic lab reports of this new class of synthetic opioids surged from 43 in 2019 to 1,905 in 2024.
Families facing opioid addiction risk or attending Narcotics Anonymous meetings to sustain recovery know that the illegal street trade in drugs can shift at any time. Any movement can lead to relapse or an overdose in their community.
Researchers analyzed the DEA’s National Forensic Laboratory Information System, which covers 284 labs in all 50 states and DC, and the Center for Forensic Science Research and Education’s NPS Discovery program that tests biospecimens from crime labs and medical examiners.
The Opioid Crisis Shifts
Let’s start with the growth curve. Between 2019 and 2024, 7,117 nitazene analog reports were submitted to NFLIS from just 43 in 2019 to 1,905 in 2024. From 2019 and 2021, counts multiplied sevenfold. After that, the curve flattened, indicating that the drugs found a steady spot in the supply.
Data from NPS Discovery showed 361 nitazene-positive biospecimens, up from 11 in 2019 to 113 in 2024, increasing roughly 45% per year. Ohio and Tennessee were the first to identify nitazene fatalities. Despite the increases, nitazene still remains unscheduled because the benzimidazole ring appears in common medicines from antiparasitics to blood pressure drugs.
Defining Nitazenes
Nitazene are also called 2-benzylbenzimidazoles or simply nitazenes, are synthetics derived from etonitazene. Pharmaceutical companies first synthesized them in the 1950s while searching for alternatives to morphine, but they were never approved for clinical use because of their deadliness and poor safety profiles. Isotonitazene shows in vitro potency up to 500x that of morphine.
Today these compounds are produced in industrial laboratories overseas, sold online, then pressed into counterfeit tablets or adulterated into heroin and fentanyl powders. It’s all illegal, and the problem is made worse because fentanyl test strips can’t detect them in the first place.
Polysubstance Patterns Raise the Stakes
Nearly all nitazene biospecimens contained at least one co-detected substance and fentanyl topped the list at 54.6%. The CDC tracks nitazenes because these mixtures are complicated and unpredictable.
The researchers connect the emergence of nitazenes to the DEA’s 2018 class-wide scheduling of fentanyl-related substances. The pattern since then has seen like whack-a-mole: schedule one analog and the supply rotates to another. The authors call for stronger drug testing capacity, expanded surveillance and targeted public health interventions rather than scheduling alone.
Harm Reduction & Treatment
Despite nitazene’s deadliness, victims aren’t totally helpless. Naloxone reverses nitazene overdoses, but multiple doses are needed with multiple drugs. Assume any powder or pill contains synthetic opioids. Keep naloxone within reach and tell folks where it’s stored..
Medication remains effective for long-term recovery. Methadone and buprenorphine reduce cravings and mortality risks.
Peer support through NA meetings adds the ongoing structure that helps people stay in treatment while the supply keeps shifting.
Narcotics Anonymous Still a Top Choice
Getting started is made easier by browsing our online directory. Search by location and find formats that fit your circumstances.
An expert can guide you through local options once you dial 800-934-1582(Sponsored) .